
Vitamin C Deficiency (Scurvy)
Physiology
L-ascorbic acid (water-soluble, glucose-related). NOT endogenously synthesised (unlike vit D) — fully diet-dependent. Sources: citrus fruits(orange/lemon/grapefruit), tomatoes/potatoes; small in meat/milk; heat-labile (boiling/pasteurisation destroys). Absorbed small intestine; stored widely, most in adrenal cortex.
Redox function: L-ascorbic acid ⇌ dehydro-L-ascorbic acid + 2H⁺+2e⁻
Functions:
- Collagen synthesis — activates prolyl+lysyl hydroxylase (procollagen hydroxylation); also needed for osteoid, chondroitin sulfate, dentin, vascular endothelial cement substance
- Antioxidant — scavenges free radicals + regenerates vit E antioxidant form
- Dopamine→norepinephrine hydroxylation
- Folate — prevents tetrahydrofolate oxidation
- Iron metabolism — absorption, storage, keeps reduced/absorbable
Mechanism
No vit C → prolyl/lysyl hydroxylase inactive → procollagen can’t form stable triple helix/cross-links → poorly secreted from fibroblasts; secreted collagen = weak tensile strength, more soluble, degradation-prone. Collagen has HIGHEST hydroxyproline content of any protein → most affected, esp. blood vessel walls → bleeding tendency. Also independently suppresses collagen polypeptide synthesis (beyond hydroxylation).
2 peak ages: early childhood + very elderly.
Consequences by system
Haemorrhagic diathesis — ↓intercellular cement (capillary endothelium)+weak collagen → bleeding: skin, mucosa, gums, muscle, joints, subperiosteal
Skeletal (growing children, most pronounced) — defect = deranged OSTEOID FORMATION, NOT mineralisation (opposite of rickets!). Cartilage provisionally mineralises normally but osteoblastic osteoid-laying is poor → cartilage NOT resorbed → projects through widened irregular epiphyseal plates = scorbutic rosary. Worsened by subperiosteal haemorrhage/haematoma + joint bleeding.
Delayed wound healing — deranged collagen synthesis + poor fibroblast maturation + wound infection tendency
Anaemia (common, multifactorial): haemorrhage + ↓folate regeneration + deranged Fe metabolism → usually normocytic normochromic; occasionally megaloblastic(folate) or iron-deficiency-pattern(Fe)
Teeth/gums — impaired dentin formation; gums soft/swollen/bleed easily/commonly infected
Skin — follicular hyperkeratotic rash
Epidemiology/at-risk groups
Diet-abundant → rare globally now. Secondary/conditioned deficiency: elderly, live-alone, chronic alcohol use (erratic/inadequate eating) | peritoneal/haemodialysis patients | food faddists. History: “limeys” = Royal Navy nickname (lime/lemon juice prophylaxis, pre-dates ascorbic acid identification 1932).
Toxicity
Megadose “prevents common cold” = NOT supported by trials (mild relief = antihistamine effect only). Excess promptly excreted in urine but causes uricosuria + ↑iron absorption → iron overload risk.
Clinical relevance
Rickets vs scurvy = classic paired contrast: rickets=mineralisation defect (osteoid forms, doesn’t calcify); scurvy=osteoid FORMATION defect (osteoblasts fail to lay osteoid) — both give a “rosary” but opposite biochemistry (rachitic vs scorbutic rosary). 2 peak ages = both dietary-pattern-vulnerable extremes of life. Modern at-risk groups (elderly-alone, alcoholics, dialysis, food faddists) = relevant to not dismissing scurvy as “historical.” Multifactorial anaemia = teaching example of one deficiency→several simultaneous mechanisms→variable morphology.
Physiology
Vitamin C (L-ascorbic acid) is a water-soluble compound structurally related to glucose. Unlike vitamin D, humans cannot synthesise it endogenously and are entirely diet-dependent. Major sources are citrus fruits (orange, lemon, grapefruit) and some vegetables (tomatoes, potatoes), with small amounts in meat and milk; the vitamin is heat-labile, so boiling or pasteurisation depletes it. It is readily absorbed in the small intestine and stored in many tissues, most abundantly in the adrenal cortex.
Vitamin C’s physiologic role centres on its capacity for reversible oxidation-reduction (L-ascorbic acid ⇌ dehydro-L-ascorbic acid + 2H⁺ + 2e⁻):
- Collagen synthesis — required to activate prolyl and lysyl hydroxylase, the enzymes that hydroxylate procollagen; also needed for the ground substance of other mesenchymal structures (osteoid, chondroitin sulfate, dentin, vascular endothelial cement substance).
- Antioxidant — scavenges free radicals directly, and participates in regenerating the antioxidant form of vitamin E.
- Catecholamine synthesis — hydroxylation of dopamine to norepinephrine.
- Folate metabolism — maintains folic acid levels by preventing oxidation of tetrahydrofolate.
- Iron metabolism — assists absorption, storage, and keeping iron in its reduced (absorbable) state.
Mechanism of Scurvy
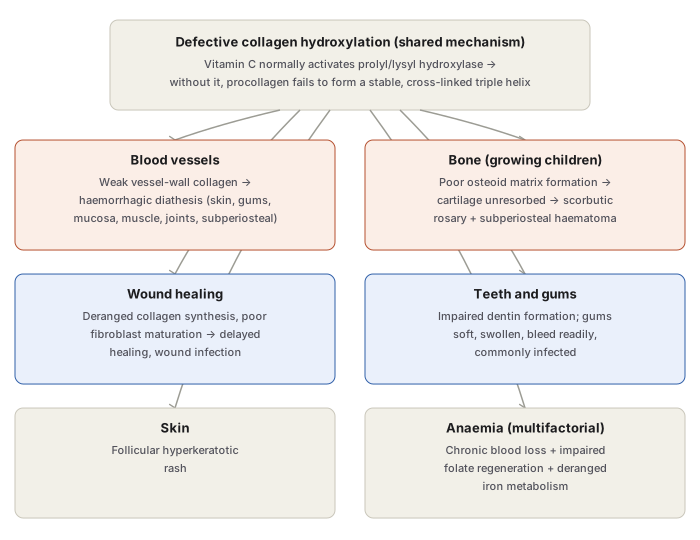
Without vitamin C, prolyl/lysyl hydroxylase remain inactive, so procollagen cannot acquire a stable triple-helical configuration or adequate cross-linking. Poorly hydroxylated procollagen is secreted inefficiently from fibroblasts, and whatever collagen does reach the extracellular space lacks tensile strength, is more soluble, and is more vulnerable to enzymatic degradation. Collagen normally has the highest hydroxyproline content of any protein, so it is disproportionately affected — particularly in blood vessel walls, explaining scurvy’s hallmark bleeding tendency. Vitamin C deficiency also independently suppresses collagen polypeptide synthesis, beyond just the hydroxylation defect.
Scurvy shows two peak ages: early childhood and the very elderly.
Consequences by Organ System
- Haemorrhagic diathesis — a marked bleeding tendency, classically attributed to deficient intercellular cement holding capillary endothelial cells together (in addition to the collagen defect itself); haemorrhage occurs into skin, mucous membranes, gums, muscle, joints, and beneath the periosteum.
- Skeletal lesions (most pronounced in growing children) — critically, the primary defect is deranged osteoid matrix formation, not deranged mineralisation — the opposite emphasis from rickets. At the epiphyses of growing long bones, cartilage cells normally undergo provisional mineralisation and are then resorbed as osteoblasts lay down osteoid; in scurvy, osteoblastic osteoid deposition is poor, so mineralised cartilage fails to be resorbed and projects through widened, irregular epiphyseal plates as the scorbutic rosary. Skeletal changes are further worsened by subperiosteal haemorrhage/haematoma and bleeding into joint spaces.
- Delayed wound healing — from deranged collagen synthesis, poor fibroblast preservation/maturation, and a tendency toward wound infection.
- Anaemia — common, and typically multifactorial: chronic haemorrhage, impaired folate regeneration, and deranged iron metabolism can all contribute. Usually normocytic normochromic, though occasionally megaloblastic (folate mechanism) or iron-deficiency-pattern (iron mechanism).
- Teeth and gums — impaired dentin development; gums become soft, swollen, bleed readily, and are commonly secondarily infected.
- Skin — follicular hyperkeratotic rash.
Epidemiology and At-Risk Groups
Because ascorbic acid is abundant in ordinary diets, scurvy is no longer a major global problem, but persists as a secondary/conditioned deficiency in specific groups: elderly persons, those living alone, chronic alcohol users (all characterised by erratic, inadequate eating patterns), patients on peritoneal dialysis or haemodialysis, and food faddists with highly restricted diets. Historically, “limeys” — the nickname for British Royal Navy sailors — arose because the Navy began supplying lime/lemon juice (rich in vitamin C) to prevent scurvy on long voyages, decades before ascorbic acid was chemically identified and synthesised (1932).
Toxicity (Hypervitaminosis C)
The popular belief that megadoses of vitamin C prevent or meaningfully relieve the common cold is not supported by controlled trials; any mild symptomatic relief is likely from ascorbic acid’s mild antihistamine action. Excess vitamin C is promptly excreted in urine, but can cause uricosuria and increased iron absorption, with a resulting risk of iron overload in susceptible individuals.
Clinical Relevance
- The rickets/scurvy contrast is a classic paired examination distinction: rickets is a mineralisation defect (osteoid is formed but doesn’t calcify), while scurvy is an osteoid matrix formation defect (osteoblasts fail to lay down osteoid in the first place) — both can produce a “rosary” deformity (rachitic vs scorbutic), but via opposite underlying biochemistry.
- The two peak ages (early childhood, very elderly) both make clinical sense from a dietary-pattern standpoint — restricted/erratic diets are common at both extremes of life, distinct from the middle-age population where scurvy is now rare in resource-adequate settings.
- Recognising the modern at-risk groups (elderly living alone, chronic alcohol users, dialysis patients, food faddists) is directly relevant to a diagnostic index of suspicion, since scurvy is easily missed today when clinicians assume it is a “historical” disease.
- Multifactorial anaemia in scurvy (haemorrhagic + folate + iron mechanisms) is a useful teaching example of a single nutrient deficiency producing anaemia through several simultaneous mechanisms rather than one clean textbook pathway — explaining why the anaemia’s morphology can vary between patients.
Diagram 1: Defective Collagen Hydroxylation as the Shared Mechanism of Scurvy
Draw one top box (the shared mechanism: vitamin C cofactor loss → failed procollagen hydroxylation) fanning out to six independent branch boxes in a 2-column × 3-row grid — parallel organ-specific consequences of one biochemical defect, not sequential steps of each other.
- Blood vessels — weak vessel-wall collagen → haemorrhagic diathesis.
- Bone (growing children) — poor osteoid formation → unresorbed cartilage → scorbutic rosary.
- Wound healing — deranged collagen synthesis, poor fibroblast maturation → delayed healing, infection.
- Teeth and gums — impaired dentin, fragile gum tissue.
- Skin — follicular hyperkeratotic rash.
- Anaemia — multifactorial (haemorrhage + folate + iron mechanisms).
Labels required
- The bone branch must explicitly state the defect is in osteoid matrix formation, not mineralisation — this is the detail that distinguishes scurvy’s skeletal lesion from rickets’, and dropping the distinction is the single most common error in this topic.
- The anaemia branch must list all three contributing mechanisms (haemorrhage, folate, iron) rather than naming just one — the multifactorial nature is itself the testable point, explaining why the anaemia’s morphology is not fixed.
Errors commonly made
- Describing scurvy’s bone lesion as a mineralisation defect (confusing it with rickets) rather than an osteoid-formation defect — both produce a “rosary” sign, which makes them easy to conflate, but the underlying biochemistry is the opposite of each other.
- Attributing the haemorrhagic tendency only to a vague “capillary fragility” without naming the actual mechanism — collagen hydroxylation failure specifically weakening vessel-wall structural integrity.
- Treating the anaemia as a simple, single-cause finding rather than the multifactorial consequence it actually is.
My Sticky Notes
Personal revision notes, mnemonics and reminders.
